
IPN vs. IDPN: Choosing the Right Dialysis Nutrition Therapy

July 10, 2026

Malnutrition is one of the most consistent, and most under-treated, complications in patients with End Stage Renal Disease (ESRD). When dietary counseling and oral supplements are no longer enough, two specialized parenteral nutrition therapies can restore what dialysis takes away: Intraperitoneal Nutrition (IPN) and Intradialytic Parenteral Nutrition (IDPN).


They are often confused because both deliver nutrition through the patient’s existing dialysis access, without a separate IV line. But they are not interchangeable. The right choice comes down to one clinical fact: how the patient dialyzes.


Why Malnutrition Matters in ESRD


Protein-energy wasting (PEW) affects a large share of the dialysis population and is a strong predictor of hospitalization and mortality. It develops from a combination of poor appetite, chronic inflammation, metabolic acidosis, dietary restrictions, and, critically, protein losses that happen during dialysis itself.


That last point is why oral intake alone often can’t close the gap. When a patient is losing protein through the treatment, adding nutrition into the treatment is frequently the most effective intervention. This is where IPN and IDPN come in.


What Is IPN?


Intraperitoneal Nutrition (IPN) is for patients on peritoneal dialysis (PD). A sterile, individualized amino acid solution is substituted for one or more of the patient’s standard PD exchanges. Instead of a plain dextrose dialysate, the exchange delivers protein and nutrients directly across the peritoneal membrane, replacing what PD removes, during the same exchange the patient already performs.


Because IPN uses the existing peritoneal catheter, there are no additional needle sticks, no IV lines, and no changes to the patient’s PD schedule. It’s compatible with both CCPD (cycler) and CAPD (manual) regimens. Learn more about Pharmko’s Intraperitoneal Nutrition (IPN) therapy and how it’s compounded.


What Is IDPN?


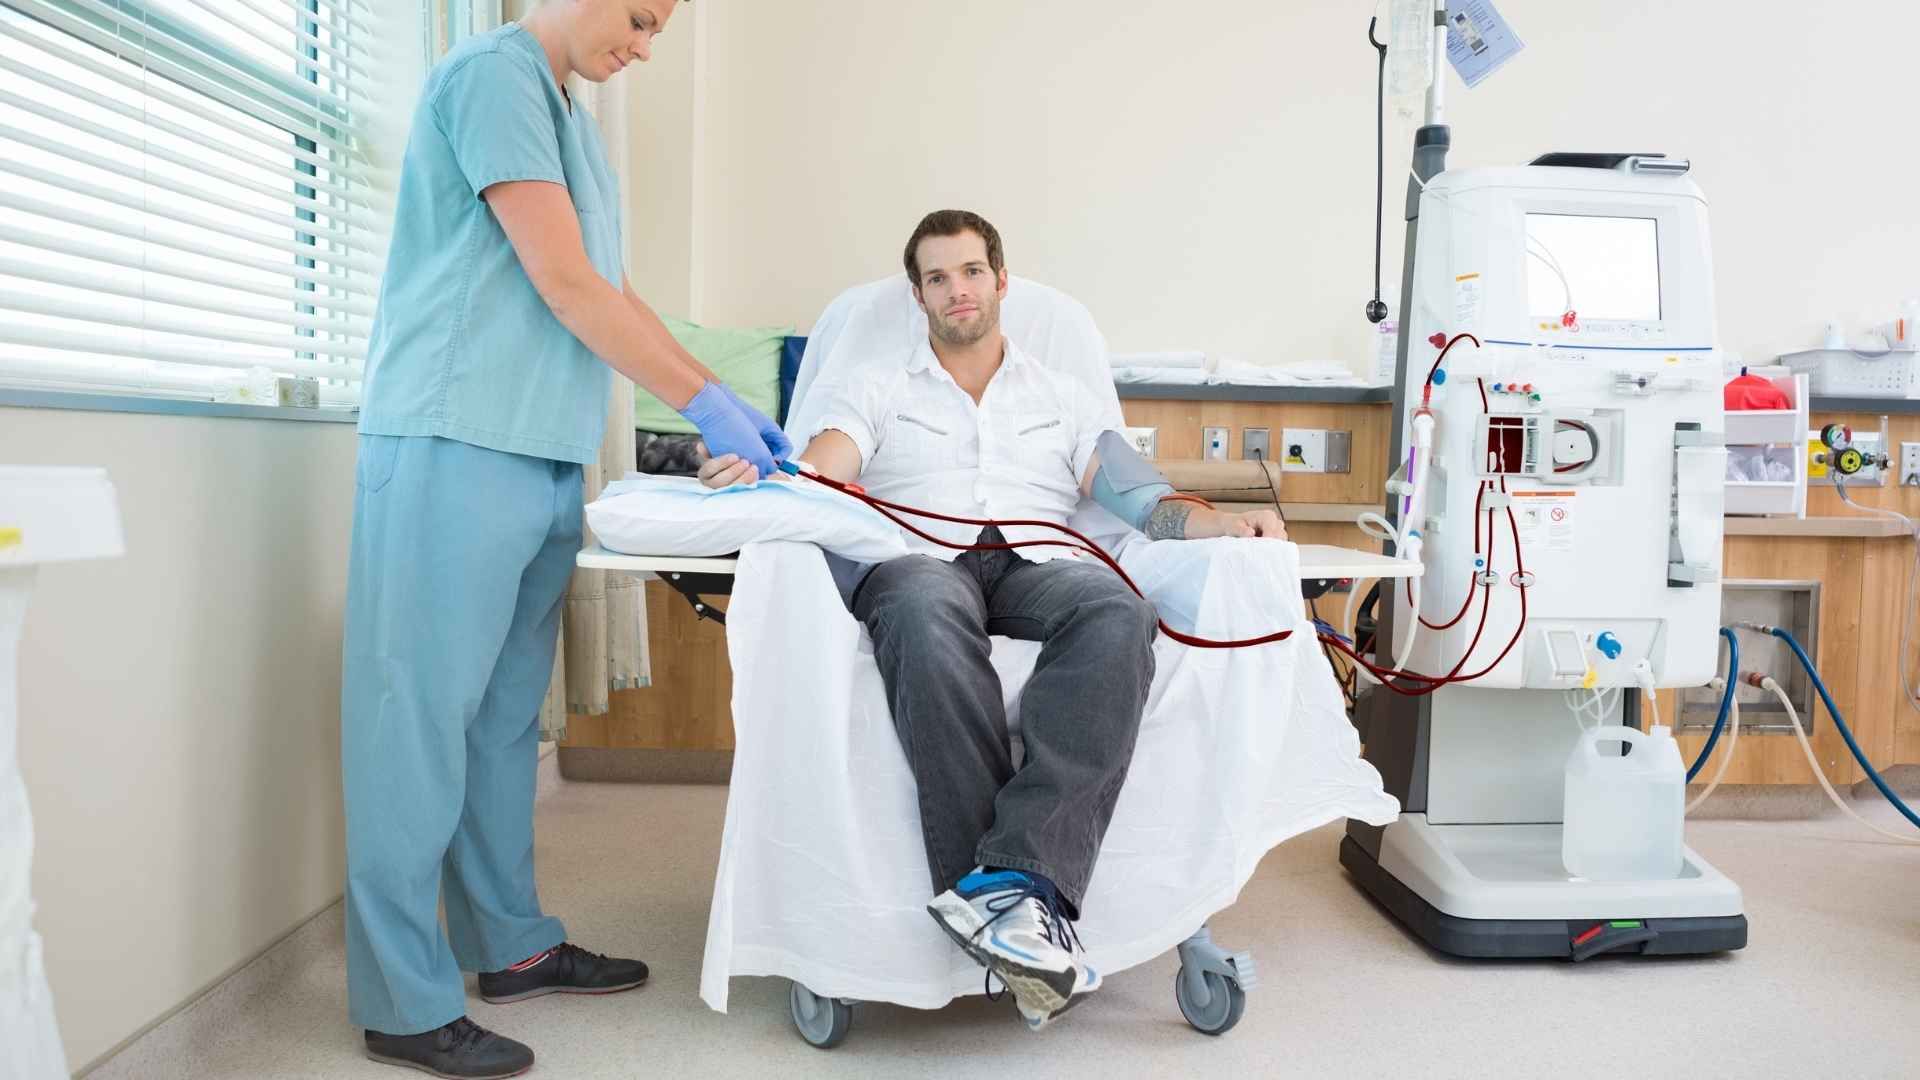
Intradialytic Parenteral Nutrition (IDPN) is for patients on hemodialysis (HD). Amino acids, dextrose, and lipids are infused into the venous drip chamber of the hemodialysis circuit during the patient’s regular treatment, typically three times per week, delivering supplemental calories per session.


Like IPN, IDPN requires no separate access: it uses the dialysis circuit that’s already in place, and the infusion pump integrates into the treatment without adding IV poles or workflow burden. See Pharmko’s Intradialytic Parenteral Nutrition (IDPN) therapy for the full clinical process.


How to Choose: A Simple Clinical Framework


Selecting between the two therapies is rarely ambiguous, because the patient’s dialysis modality usually decides it. A practical way to think about it:


1. Start with the modality. Peritoneal dialysis → IPN. Hemodialysis → IDPN. This single question resolves most cases.


2. Confirm the nutritional indication. Both therapies are appropriate when a patient shows persistent malnutrition, commonly serum albumin below 3.5 g/dL, unintentional weight or muscle loss, or inadequate intake, despite first-line dietary counseling and oral nutritional supplements.


3. Confirm first-line measures were tried. IPN and IDPN are not first steps. Clinical guidelines support a stepwise approach: dietitian-led counseling, then renal-specific oral supplements, then parenteral nutrition when those are insufficient or not tolerated.


4. Rule out reversible causes. Neither therapy is a substitute for correcting underdialysis, inflammation, or acidosis. These should be optimized alongside nutrition therapy, not replaced by it.


What About TPN?


A third therapy, Total Parenteral Nutrition (TPN), is sometimes part of the conversation, but it addresses a different problem. TPN provides complete nutrition through a central venous catheter for patients whose GI tract can’t be used at all. IPN and IDPN are supplemental, targeted specifically at the nutrition dialysis removes. Most dialysis patients who can still eat, but can’t keep up, are candidates for IPN or IDPN rather than TPN.


The Pharmko Difference


Both IPN and IDPN are only as good as the formulation and the coordination behind them. Every Pharmko solution is compounded in our USP <797>-compliant, ISO Class 5 cleanroom, individualized to the patient’s labs, dialysis prescription, and nutritional status — never a standard premix. Our pharmacists work directly with nephrologists, renal dietitians, and PD/dialysis nurses, review labs on an ongoing basis, and adjust formulas as the patient’s needs change. We also handle prior authorizations and delivery logistics end to end.


Whether your patient dialyzes at home or at a center, the goal is the same: replace what dialysis removes, with as little burden on the patient as possible.


Ready to match a patient to the right therapy? Explore Pharmko’s dialysis and renal nutrition program or refer a patient today.


Refer a Patient  · [1 (877) 540-2003]


Person living with end stage renal disease going about an ordinary morning at home
September 1, 2026
Straight answers to what people on dialysis ask most: nutrition, phosphate, energy, travel, and the emotional weight of ongoing treatment.

Handwritten list of questions prepared for a dialysis appointment about IDPN therapy
September 1, 2026
The questions worth bringing to your nephrologist or dietitian before starting intradialytic parenteral nutrition, grouped and ready to print.

Adult daughter and her mother reviewing a delivery schedule together in the kitchen at home
September 1, 2026
A practical guide for caregivers: what your role is, what the pharmacy can share with you, what to keep track of, and how to protect your own energy.

Family sharing a meal at home while one member on parenteral nutrition joins the table
September 1, 2026
Whether you can eat on parenteral nutrition, why appetite and taste change, and how to handle meals with family while receiving IV nutrition.
Suitcase packed with a small cooler and paperwork for traveling while on parenteral nutrition
August 31, 2026
How to plan a trip on TPN or home parenteral nutrition: supplies, refrigeration, air travel documentation, and how far ahead to call your pharmacy.
Home delivery of TPN supplies unpacked on a kitchen table during the first week of therapy
August 31, 2026
A day-by-day look at starting total parenteral nutrition at home: the first delivery, the first infusion, night one, and when to call for help.

Dialysis center staff coordinating phosphate binder supply with a pharmacy partner
August 11, 2026
What dialysis centers should look for in a phosphate binder supply partner: reliable delivery, formulary breadth, insurance support, and coordination.
Renal dietitian reviewing phosphate levels with a dialysis patient
August 11, 2026
How hyperphosphatemia is managed in ESRD dialysis patients, diet, dialysis, and phosphate binders, and why reliable binder supply keeps therapy on track.

July 29, 2026
Compounded medications are a routine part of modern care, but unlike mass-manufactured drugs, each one is prepared individually, which means the standards behind its preparation carry real weight. For providers who order or refer for compounded therapies, a working understanding of those standards is the clearest way to judge whether a pharmacy is safe to trust. This overview covers the standards that govern sterile compounding and what they mean for the medications your patients receive. Why Standards Matter More in Compounding A commercially manufactured drug is produced under FDA oversight in large, validated batches. A compounded medication is prepared for an individual patient, often in small quantities, sometimes because no commercial equivalent exists. That flexibility is exactly why it's clinically valuable — and why the standards around preparation exist. Without rigorous controls, the same customization that helps patients could introduce contamination or error. Our guide to our sterile compounding pharmacy describes how those controls come together in practice. The Regulatory Landscape Sterile compounding sits within a layered framework: The United States Pharmacopeia (USP) publishes the general chapters, most importantly <797> and <800>, that define how compounded preparations should be made and handled. State boards of pharmacy license and inspect pharmacies, including where they're permitted to ship. Multi-state operations must maintain licensure in each state they serve. Accreditation bodies (ACHC, NABP, PCAB) provide independent verification that a pharmacy meets recognized standards. Together, these create the accountability structure behind every compounded dose. USP <797>: Sterile Preparations USP <797> is the cornerstone standard for compounded sterile preparations. It governs the conditions and practices required to keep a preparation free of contamination, including personnel training and garbing, ISO-classified air quality and engineering controls, environmental monitoring, and beyond-use dating. For any medication infused directly into the body, <797> compliance is the baseline expectation, not a premium feature. USP <800>: Hazardous Drugs USP <800> adds a containment layer for hazardous drugs, protecting personnel, patients, and the environment from unintended exposure. It specifies containment engineering controls, PPE, and validated handling procedures for drugs identified as hazardous. When a preparation is both sterile and hazardous, it must satisfy <797> and <800> together. For the details, see our breakdown of USP <800> requirements . Accreditation: Independent Verification Standards are only meaningful if someone checks that they're being met. Accreditation from ACHC, NABP, and PCAB means a pharmacy has been inspected against national benchmarks by an outside authority. For a provider, accreditation is a shortcut to confidence: it signals that the pharmacy's claims about its processes have been independently validated. The Quality-Control Process Behind the standards is a repeatable process that governs each preparation: Pharmacist review of the prescription for appropriateness, compatibility, and dosing Preparation by trained technicians under aseptic conditions In-process and final verification by a licensed pharmacist Sterility testing or filtration validation where required This chain is what turns a standard on paper into a safe medication in a patient's hands. What This Means When You Order When you refer a patient for a compounded therapy, you're effectively extending your own standard of care into another facility. Knowing that a pharmacy is USP-compliant, accredited, and pharmacist-led lets you refer with confidence that the medication will meet the same expectations you'd hold for anything you administer yourself. If you're weighing options, our guide on how to choose a compounding partner walks through the criteria. The Pharmko Standard Pharmko compounds every TPN, IDPN, and IPN preparation in a USP <797>-compliant, ISO Class 5 cleanroom, under ACHC, NABP, and PCAB accreditation, with a licensed pharmacist reviewing and releasing each formula. For the patients who receive our preparations, many of them managing End Stage Renal Disease (ESRD), that standard is the point. Refer a Patient → · [1 (877) 540-2003]

Physician evaluating a sterile compounding pharmacy partner
July 29, 2026
How to evaluate a sterile compounding pharmacy: accreditation, USP compliance, clinical support, turnaround, and the questions every practice should ask.

Show More


