

Straight answers to what people on dialysis ask most: nutrition, phosphate, energy, travel, and the emotional weight of ongoing treatment.

The questions worth bringing to your nephrologist or dietitian before starting intradialytic parenteral nutrition, grouped and ready to print.

A practical guide for caregivers: what your role is, what the pharmacy can share with you, what to keep track of, and how to protect your own energy.

Whether you can eat on parenteral nutrition, why appetite and taste change, and how to handle meals with family while receiving IV nutrition.

How to plan a trip on TPN or home parenteral nutrition: supplies, refrigeration, air travel documentation, and how far ahead to call your pharmacy.

A day-by-day look at starting total parenteral nutrition at home: the first delivery, the first infusion, night one, and when to call for help.

What dialysis centers should look for in a phosphate binder supply partner: reliable delivery, formulary breadth, insurance support, and coordination.
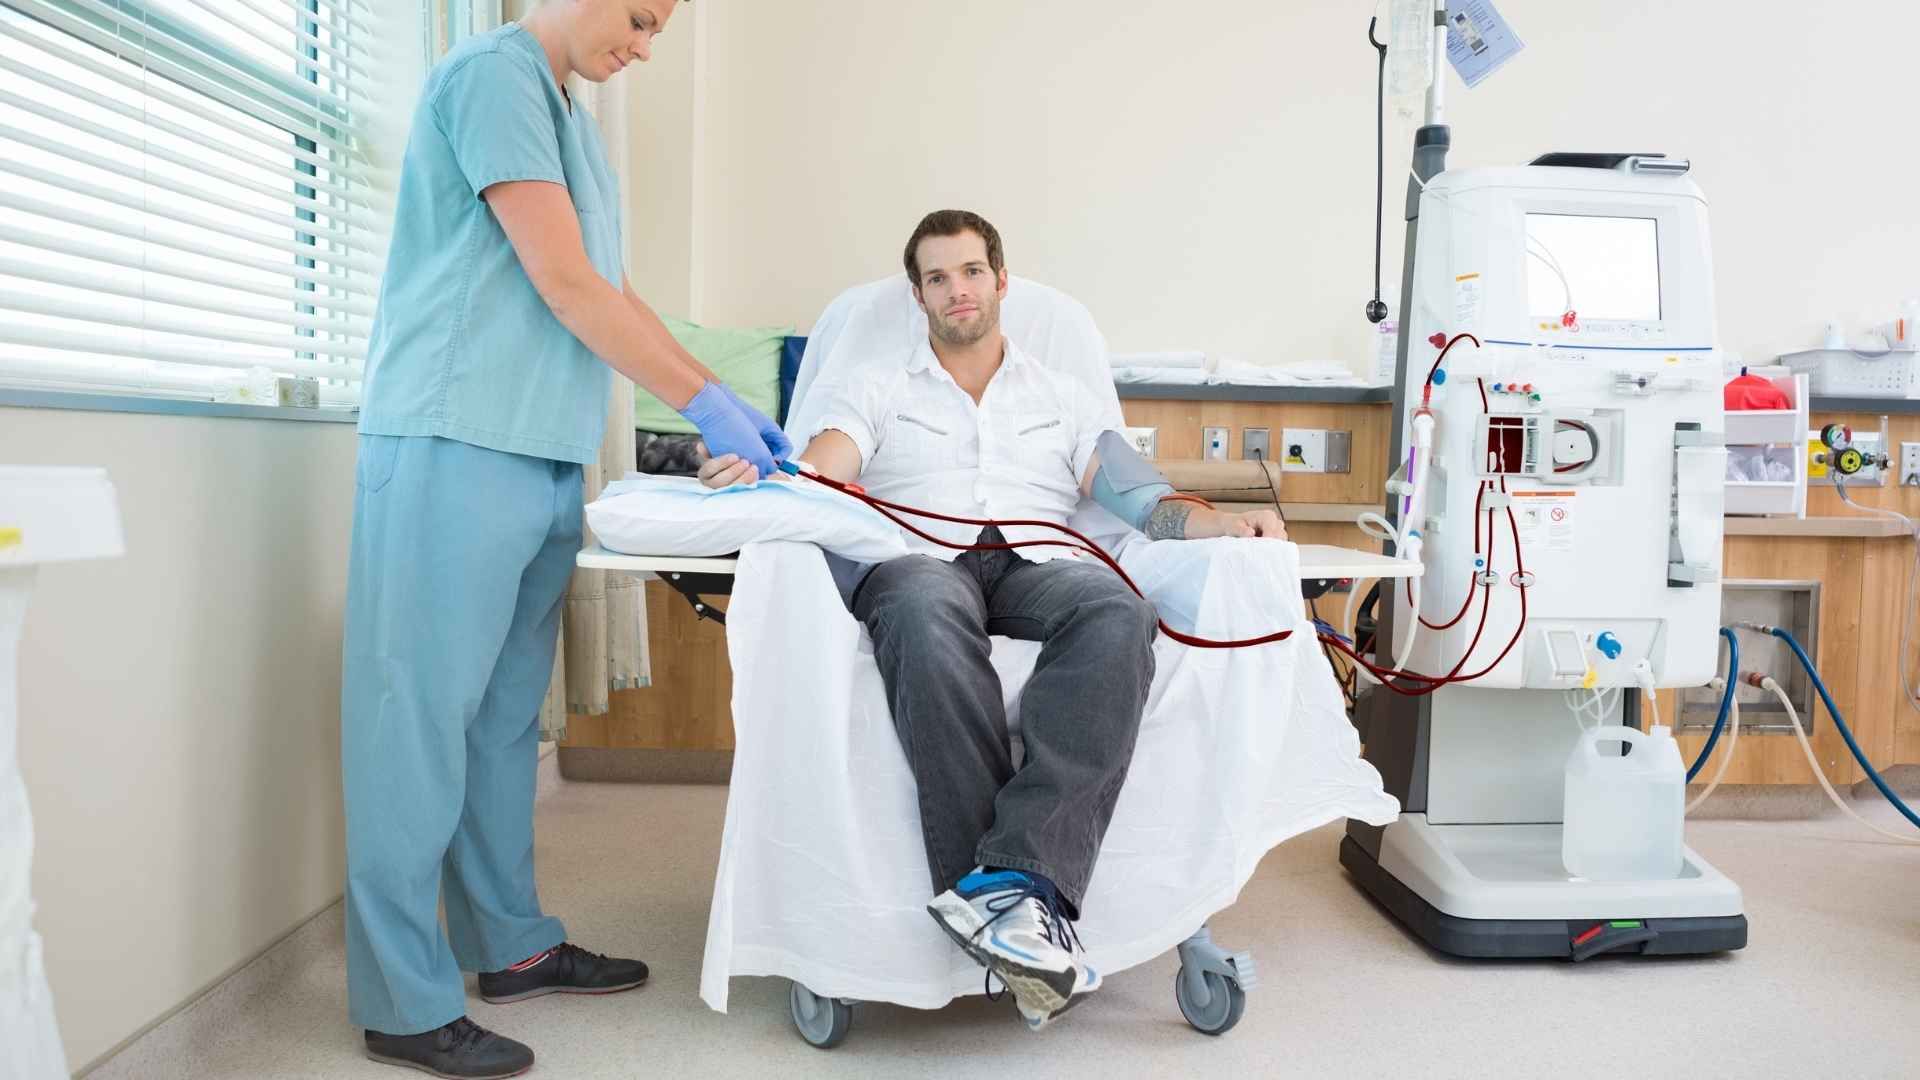
How hyperphosphatemia is managed in ESRD dialysis patients, diet, dialysis, and phosphate binders, and why reliable binder supply keeps therapy on track.

Compounded medications are a routine part of modern care, but unlike mass-manufactured drugs, each one is prepared individually, which means the standards behind its preparation carry real weight. For providers who order or refer for compounded therapies, a working understanding of those standards is the clearest way to judge whether a pharmacy is safe to trust. This overview covers the standards that govern sterile compounding and what they mean for the medications your patients receive. Why Standards Matter More in Compounding A commercially manufactured drug is produced under FDA oversight in large, validated batches. A compounded medication is prepared for an individual patient, often in small quantities, sometimes because no commercial equivalent exists. That flexibility is exactly why it's clinically valuable — and why the standards around preparation exist. Without rigorous controls, the same customization that helps patients could introduce contamination or error. Our guide to our sterile compounding pharmacy describes how those controls come together in practice. The Regulatory Landscape Sterile compounding sits within a layered framework: The United States Pharmacopeia (USP) publishes the general chapters, most importantly <797> and <800>, that define how compounded preparations should be made and handled. State boards of pharmacy license and inspect pharmacies, including where they're permitted to ship. Multi-state operations must maintain licensure in each state they serve. Accreditation bodies (ACHC, NABP, PCAB) provide independent verification that a pharmacy meets recognized standards. Together, these create the accountability structure behind every compounded dose. USP <797>: Sterile Preparations USP <797> is the cornerstone standard for compounded sterile preparations. It governs the conditions and practices required to keep a preparation free of contamination, including personnel training and garbing, ISO-classified air quality and engineering controls, environmental monitoring, and beyond-use dating. For any medication infused directly into the body, <797> compliance is the baseline expectation, not a premium feature. USP <800>: Hazardous Drugs USP <800> adds a containment layer for hazardous drugs, protecting personnel, patients, and the environment from unintended exposure. It specifies containment engineering controls, PPE, and validated handling procedures for drugs identified as hazardous. When a preparation is both sterile and hazardous, it must satisfy <797> and <800> together. For the details, see our breakdown of USP <800> requirements . Accreditation: Independent Verification Standards are only meaningful if someone checks that they're being met. Accreditation from ACHC, NABP, and PCAB means a pharmacy has been inspected against national benchmarks by an outside authority. For a provider, accreditation is a shortcut to confidence: it signals that the pharmacy's claims about its processes have been independently validated. The Quality-Control Process Behind the standards is a repeatable process that governs each preparation: Pharmacist review of the prescription for appropriateness, compatibility, and dosing Preparation by trained technicians under aseptic conditions In-process and final verification by a licensed pharmacist Sterility testing or filtration validation where required This chain is what turns a standard on paper into a safe medication in a patient's hands. What This Means When You Order When you refer a patient for a compounded therapy, you're effectively extending your own standard of care into another facility. Knowing that a pharmacy is USP-compliant, accredited, and pharmacist-led lets you refer with confidence that the medication will meet the same expectations you'd hold for anything you administer yourself. If you're weighing options, our guide on how to choose a compounding partner walks through the criteria. The Pharmko Standard Pharmko compounds every TPN, IDPN, and IPN preparation in a USP <797>-compliant, ISO Class 5 cleanroom, under ACHC, NABP, and PCAB accreditation, with a licensed pharmacist reviewing and releasing each formula. For the patients who receive our preparations, many of them managing End Stage Renal Disease (ESRD), that standard is the point. Refer a Patient → · [1 (877) 540-2003]

How to evaluate a sterile compounding pharmacy: accreditation, USP compliance, clinical support, turnaround, and the questions every practice should ask.



